
What is a dental implant, and who is it for?
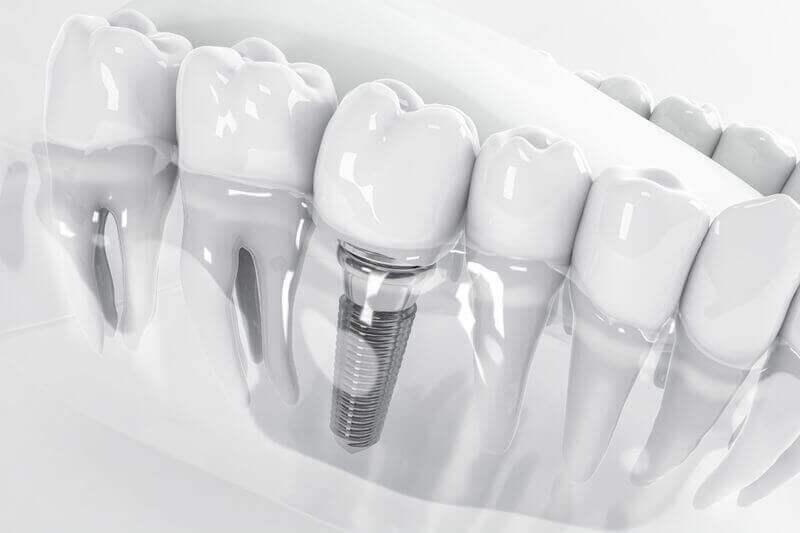
A dental implant is an artificial root, usually a titanium screw, placed in the jawbone where a tooth is missing. Once it has fused with the bone, a crown or bridge is fixed on top. It is considered for people missing one or a few teeth whose bone and gums are suitable. The neighbouring teeth are not ground down. It is surgery, and it does not suit everyone.
This page covers one missing tooth or a few. If a whole jaw has no teeth, or its remaining teeth cannot be saved, see full-mouth dental implants. Fixed bridges on four or six implants are explained under All-on-4 and All-on-6. Below: who it suits, the options, the stages, the risks, how long implants have lasted in studies, and what changes if you travel for treatment. On this page, "we" means our clinic in Antalya, Turkey. Every study figure on this page is linked to its source. Those figures come from published studies, not from our own records.
- An implant fills the gap left by a missing tooth without grinding down the neighbouring teeth; it is a surgical option.
- For single missing teeth, about 97 in 100 implants were still in the mouth after five years and about 95 in 100 after ten.
- Being in place is not the same as being trouble-free: loose screws, gum problems and chipped porcelain were reported within five years.
- An implant is not the only way: saving the tooth, a bridge, a partial denture or doing nothing are options too.
- Smoking, a history of periodontitis and clenching are associated with losing implants.
Who it suits, and who it does not
Where it may be suitable
- Adults missing one or a few teeth whose general health allows surgery and healing
- Enough bone height and width to hold the implant; where there is not, bone grafting or a sinus lift may be considered
- Healthy gums, or gum treatment already completed
- People who do not want their neighbouring teeth ground down
- People who cannot manage or do not want a removable partial denture
What is associated with higher risk
The figures below are pooled results of observational studies; they show association, not proven causation.
- Smoking. A 2020 review compared people who smoked more than 20 cigarettes a day with non-smokers. They had about 2.5 times the risk of implant loss per implant1; per patient, the risk was about 4 times higher1. In that review the risk rose with the number of cigarettes, and no level of smoking was shown to be free of extra risk. For early implant loss in smokers, a review of 32 studies gave an odds ratio of 2.59 per implant2. It comes from the 21 groups of patients analysed per implant. An odds ratio compares odds, not risks, so this does not mean that the absolute risk is 2.6 times higher.
- A history of periodontitis (gum disease that has damaged the bone around the teeth). Across 14 prospective studies, implants were lost at about 1.75 times the rate3 seen in people without that history. After fast-progressing disease the rate was about 6 times higher3. These are hazard ratios, not absolute risks. Peri-implantitis (inflammation around the implant with bone loss) was about 3 times more likely3. These were treated patients; implants are not placed while the disease is active.
- Clenching or grinding. Across 27 studies, people judged likely to clench or grind their teeth were compared with people who do not. The odds of implant loss were about 2.2 times higher4 in the first group (an odds ratio). These studies did not test whether a night guard prevents that.
- Diabetes. The findings are mixed. Two of three reviews found no significant difference in implant loss: a nine-study review of type 2 diabetes5 and an older review6. The third, covering 89 publications, reported a higher odds ratio7 for implant loss. All three found more bone loss around implants in people with diabetes. That is why blood-sugar control and regular reviews matter.
- Bone-strengthening medicines (bisphosphonates, denosumab). The risk depends on why the medicine is taken, and on its dose, route and duration. Whether it is given by drip, by injection or by mouth does not on its own decide it. In people on high-dose antiresorptive treatment for cancer, elective implant surgery is usually avoided. That group includes bisphosphonates given by drip and denosumab given by injection under the skin. The decision is made together with your oncology and oral surgery teams. Do not stop a medicine without asking the doctor who prescribed it. Doses used for osteoporosis, whether tablets, infusions or injections, are assessed separately. With these medicines the main concern is medication-related death of jaw bone (osteonecrosis), an area of jawbone that dies and may not heal. Separately, a 21-study review looked at people taking bisphosphonates as one group, not by the reason they took them. In it, implant loss was about 1.7 times more likely per implant8. Jaw osteonecrosis was about 3.5 times more likely per patient8. The per-patient analysis of implant loss found no significant difference. These figures are for bisphosphonates and cannot be applied to denosumab; the certainty of the evidence is very low. Tell us about every medicine you take.
- Radiotherapy to the head and neck. Implants are lost more often in irradiated bone. After extractions and implant surgery there is a risk of wounds that do not heal and of bone death (osteoradionecrosis). We ask about the field and dose of your radiotherapy, and planning is done with your oncology team.
Where another step comes first
- A tooth that can be saved. Whether the tooth can be kept is assessed first. If root canal treatment, gum treatment or a crown could keep it, that comes first. Before you agree to an extraction, ask about the tooth's outlook and the ways of replacing it, an implant among them.
- Active infection, untreated gum disease, uncontrolled medical conditions. These are dealt with first.
- Not enough bone. For one or a few missing teeth, bone grafting or a sinus lift may be considered; both lengthen treatment and carry their own risks. In some cases short implants are an alternative; the options without a graft are compared on the bone grafting page. Zygomatic implants are not the subject of this page. They are a separate method, considered for people with no teeth in an upper jaw whose bone has been severely lost.
- A jaw that is still growing. In young patients, implants wait until growth is complete.
Suitability is decided by an examination, a 3D scan and your medical history. A plan based on photographs or a panoramic X-ray is not final; it is a preliminary assessment.
Options: an implant is not the only way
There is more than one way to deal with a missing tooth, or one that cannot be saved. The list starts with the option that removes the least tissue.
- Doing nothing. For a single missing back tooth, this is a reasonable option for some people. The trade-off: over time the teeth either side of the gap can drift, and the opposing tooth can over-erupt. The bone in the gap also shrinks. Discuss this option with your dentist too.
- Saving the tooth. If the tooth is still there, ask first whether root canal treatment, gum treatment, a repair or a crown could keep it. Keeping your own tooth usually preserves the most natural tissue.
- A removable partial denture. It is used for people who do not want surgery, or for whom surgery is not suitable. It is not a second-class solution; it is an option with its own indications. You take it out to clean it, and getting used to it takes time.
- A resin-bonded (adhesive) bridge. For suitable single-tooth gaps, a bridge with a wing bonded to the back of the neighbouring tooth can be used. It needs very little or no grinding of that tooth, and no surgery. It does not suit every gap or every bite; it can come loose and may need re-bonding.
- A conventional tooth-supported bridge. The teeth either side of the gap are reduced and a bridge is made over them. If those teeth are healthy, the tissue removed does not grow back. On the other hand, no surgery is needed and the treatment is short.
- An implant crown or bridge. The neighbouring teeth are not ground down to support it. It needs surgery and a healing period. Where several teeth are missing, not every gap needs its own implant; a bridge can be made on a few implants.
Which option suits you depends on where the gap is, the state of the neighbouring teeth, the bone, your bite and your habits. If you have been offered only one option, ask why the others were ruled out.
| Removable partial denture | Conventional tooth-supported bridge | Implant crown or bridge | |
|---|---|---|---|
| What happens to the neighbouring teeth? | Clasps rest on the neighbouring teeth; grinding is usually minimal | The neighbouring teeth are reduced; the tissue removed does not grow back | The neighbouring teeth are not ground down to support it |
| Surgery | None | None | Yes; more surgery if there is not enough bone |
| Waiting period | Short | Short | Waiting for the implant to fuse with the bone; depends on the plan |
| Bone in the gap | Shrinkage continues | Shrinkage continues | Does not fully prevent the loss after extraction; some loss is expected |
| Care | Take out and clean; gums and supporting teeth are checked | Cleaning under the bridge | Measurements around the implant, cleaning between the teeth; review programme |
| Further work | Relining, clasp repair, replacement | Decay or root canal problems in the supporting teeth; replacing the bridge | Screw loosening, chipped porcelain, replacing the crown |
| When it is not suitable | Strong gag reflex, poor retention | Less suitable when the neighbouring teeth are healthy and untouched, as sound tissue is removed; an adhesive bridge is then also considered | When bone, gums or general health do not allow it |
How the treatment runs
Implant treatment has two main stages, the surgery and the crown or bridge, with healing in between. The number of visits and the length of each depend on you and your plan; both should be written in the plan. Travel is covered in 'If you are coming from abroad' below, and sedation on the anaesthesia and sedation page. When the restoration is complete, probing measurements around the implant and an X-ray are taken as a baseline record9. The 2017 international consensus report on diseases around implants recommends this.
Examination, 3D scan and medical history
The gap, the neighbouring teeth, the gums and the bone are assessed, with a 3D scan showing where the sinus and nerve canal lie. We ask about smoking, diabetes, gum disease, clenching, medicines and radiotherapy. The plan is given in writing, with the options and the reasoning.
Preparation
Active decay, infection and gum disease are treated first. If a tooth needs to come out, the timing is decided here, including whether the implant goes in at the same session or later. If you want sedation, the escort and fasting rules are explained in advance.
Surgery: placing the implant
Under local anaesthetic, with conscious sedation if you wish, the gum is opened, a site is prepared in the bone and the implant placed. A bone graft can be placed in the same session if needed. The gum is then closed; not every patient needs stitches.
Check after surgery
The area is checked after surgery. If you have stitches that need removing, ask when and where that is done, and whether it falls before your flight home. You are given eating and cleaning instructions for the healing period, including what to do if a temporary tooth was fitted on the implant.
Healing
The implant needs time to fuse with the bone. How long depends on bone density, the implant's position, any graft and how you heal. It is often shorter in the lower jaw than in the upper. You are told your own period after the examination. What you wear in the meantime is explained below.
Healing cap and impressions
Once fusion is confirmed, a healing cap may be fitted to shape the gum. Then an impression or a digital scan of the mouth is taken, and the shade and shape are chosen.
The final crown or bridge
The crown or bridge is screwed or cemented onto the implant. The bite is adjusted, and you are shown how to clean between the teeth. A screw-retained crown can be removed when needed.
Review programme
When the restoration is complete, probing measurements around the implant and an X-ray are recorded as a baseline; later changes are compared with this record. Without it, peri-implantitis can only be judged against a general threshold. Your review interval is set by your risk and given in writing. If a dentist at home will see you for reviews, take this record to them.
What is in your mouth while you wait?
This matters day to day, and the answer is not the same for everyone. One of these is chosen for the waiting period:
- The gap is left empty. Some people choose this for back teeth that do not show.
- A removable temporary denture. A small removable piece is made for one or a few teeth. You take it out, and it is adjusted so that it does not press on the healing area.
- A bonded temporary bridge. Where suitable, a thin temporary bridge attached to the neighbouring teeth can be used.
- A temporary tooth on the implant. This is done only in selected patients, if the implant holds firmly enough in the bone at placement (primary stability).
The last option is not for everyone; its risks, and whether it is in your plan, should be discussed separately. A Cochrane review of 26 randomised trials found no convincing difference10 within one year between loading an implant immediately and waiting. Most of its trials were at high or unclear risk of bias. Another review of 39 randomised trials reported slightly lower implant survival11 with immediate loading. The decision depends on how firmly the implant holds during surgery, and on you.
Which of these you will have, and whether it is included in your plan, should be written in your treatment plan. If it is not, ask for it in writing. If a fixed temporary tooth is planned, ask what you will have instead if the implant is not stable enough at surgery. Ask too whether that changes the cost or the trips. If you are travelling, this is what you will live with at home between trips, so settle it before you book.
Which implant is used, and what to ask
There are many different implant systems. Surface treatment, screw design, the range of parts and the availability of the parts that go on top differ from system to system. The 2017 consensus report, which defined the diseases around implants, also noted that there is no generic implant9. There are numerous implant designs, with different surfaces. As well as the brand name, ask whether the parts of that system can still be obtained years from now.
When you receive a quote, ask for these in writing:
- Which system is planned, and in which diameter and length?
- Is the part that goes on top (the abutment) from the same system?
- Will a dentist in my own country be able to obtain these parts years from now?
- Will I be given an implant card or a similar record?
- If the plan offers an 'upgraded' option, what changes, and why is it needed?
A brand name alone does not decide the result. Published survival rates are not the results of one brand, clinic or dentist either; they are averages pooled from different countries and different patient groups. We give you the systems we use, and the one planned for you, in writing in your treatment plan.
Risks and benefits
Risks
The figures below come from published studies, not from our own records.
- Implant loss. A review of 46 studies looked at implants carrying a single crown. Of every 100, about 97 were still in the mouth after five years and about 95 after ten12. The rest were lost. The ten-year figure is an estimate from a statistical model. It is not always possible to place a new implant where one was lost; further surgery or a different restoration may be needed.
- Inflammation around the implant. Peri-implant mucositis is inflammation of the soft tissue around an implant. Peri-implantitis is that inflammation together with loss of the supporting bone. Its treatment may need surgery, and if it is not controlled, further bone loss can lead to losing the implant. A 57-study review reported peri-implantitis in about 20 in 100 patients and about 12 in 100 implants13. An older 11-study review found mucositis in about 43 in 100 patients14. The rates vary widely with the definition used.
- Technical and biological problems. The same review reported these cumulative five-year rates: screw loosening 8.8 percent, soft-tissue problems 7.1 percent and aesthetic complications 7.1 percent12. Bone loss of more than 2 millimetres was 5.2 percent, the crown coming loose (loss of retention) 4.1 percent and chipped porcelain 3.5 percent12. The review's published summary does not say, for most of these rates, whether they are counted per implant or per crown. A loose screw can be tightened and a damaged crown repaired or replaced; soft-tissue problems need assessment and treatment. Regular reviews are needed to find them.
- Surgical risks. Bleeding, swelling, bruising and infection can occur. In the lower jaw, nerves run close to where implants are placed, so the lip, chin or tongue can go numb. This is usually temporary; rarely, it does not go away. The root of a neighbouring tooth can be damaged while the implant site is prepared. In the back of the upper jaw the sinus is close. The sinus membrane can tear, sinusitis can develop, or an opening can form between the mouth and the sinus. A 3D scan and careful planning reduce these risks; they do not remove them.
- An implant placed at the same session as the extraction. A review pooling studies with different follow-up and patient selection found survival of 95.2 percent15 for implants placed straight into the extraction socket. For implants placed in healed bone it was 98.4 percent15 (per implant). This is a group average, not a personal probability for you. The review's authors ask for the method to be used with caution. The decision depends on the state of the tooth and the bone.
- Limits of appearance. At the front of the mouth, the shape of the gum, the lip line and the colour of the neighbouring teeth decide the result. The gum can recede over time, and the metal edge of the implant can then show. Your expectations are discussed before treatment.
Benefits
- The neighbouring teeth are not ground down; no healthy tooth is reduced for a bridge.
- The implant passes chewing load to the bone. This does not fully prevent the bone loss that follows an extraction. Bone can also be lost around the implant over time or through disease.
- It is fixed: you do not take it out, and there are no denture clasps. A screw can still loosen or the crown come loose, as the figures above show. It does not feel or work exactly like a natural tooth.
- Where several teeth are missing, a bridge can be carried on fewer implants than there are missing teeth.
After surgery and daily care
The first days
- Swelling and bruising usually increase over the first 48 to 72 hours, then settle. Use cold packs and the medicines prescribed.
- Choose soft, lukewarm food for the first days, and do not chew on the surgical site.
- Do not stop cleaning your mouth. Clean the surgical area the way your dentist shows you, and the rest of your mouth as usual.
- If you had sedation, do not drive or operate machinery for as long as the sedation team tells you. Whether you need an escort depends on the method. A UK national standard covers conscious sedation in dentistry. For adults, it says that every form of sedation other than inhalation sedation requires a responsible adult as an escort16. It also says that if an escort cannot be assured, treatment under sedation must not be provided. If you are travelling alone and want sedation, raise this before you book. Before you leave the clinic after surgery, you and your escort should have written aftercare instructions. You should also know how to reach the clinic, including out of hours.
- Smoking is associated with poorer healing. At the very least, do not smoke during the healing period.
Flying
A 2023 narrative review suggests waiting at least 72 hours17 after implant placement before flying. After a sinus lift it suggests at least two, and ideally six, weeks17. These intervals assume no pain, swelling or bleeding at the treated site. The authors say the research is limited and comes mostly from military aviation. Treat these intervals as a starting point for a conversation with the dentist who treated you, not as clearance. Your written plan proposes flight dates on this basis; confirm them with that dentist after the treatment.
Daily care
- Brush twice a day with a soft brush and fluoride toothpaste. Pay particular attention to the line where the implant meets the gum.
- Clean between the teeth every day with interdental brushes, floss or a water flosser. Your dentist shows you which works in your mouth.
- If you clench, a night guard may be advised to protect the crown or bridge. It has not been shown to prevent implant loss, and we have found no study showing how well it protects the restoration.
- Reviews. Follow-up for an implant is different from a general dental check-up. The consensus report recommends that an X-ray and probing measurements be taken as a baseline9 when the restoration is complete. The European Federation of Periodontology guideline calls for a structured supportive care programme18 once implants are in use. The UK's NICE guideline on dental recall recommends that the interval between reviews be set for each patient19. It is based on a risk assessment and discussed with the patient. That guideline covers check-ups in general, not implants. So there is no ready-made 'once a year' interval that suits everyone; yours may be shorter or different, depending on your risk.
How long does it last?
The rates below are not promises. They are pooled estimates, calculated with statistical models from studies with different lengths of follow-up. What happens in your case depends on your bone, your gum health, your habits and your care.
- The implant itself. In the 46-study review, of every 100 implants, about 97 were still in the mouth after five years and about 95 after ten12 (per implant).
- The crown on top. In the same review, of every 100 crowns, about 96 were in use after five years and about 89 after ten12 (per crown). In an older review the figures were about 95 at five years and about 89 at ten20. The rate for the implant is not the same as the rate for the tooth on top of it.
- No one can promise a lifetime result. The reviews we use give five- and ten-year estimates. The ten-year values are estimates from a statistical model, based on studies with a mean follow-up of at least five years. Longer-term reviews exist, but those we have checked cover different patient groups and restoration types, so their results are not carried over here. None of them promises a lifetime result.
- Being in place is not the same as being trouble-free. The rates above show only that the implant or the crown is still there. Regular cleaning and reviews are part of maintenance. A loose screw or chipped porcelain needs a repair, and replacing the whole crown counts as losing the restoration. Ask beforehand whether these are included in your plan.
If you are coming from abroad
We have found no good research comparing implant treatment squeezed into a few days with treatment spread over months. The nearest evidence, the Cochrane review of loading times10, followed patients for a year at most, so it cannot settle the question. The timing first has to meet clinical requirements: how firmly the implant holds and how you heal. Beyond that, judge it on practical grounds. How is healing checked? Who do you contact if something goes wrong? What aftercare is included in the plan?
Trips and days
An implant needs a healing period between the surgery and the final crown, so the treatment may not fit into one trip. Your plan states how many trips it needs, what is done on each, how many days each one takes and when you can fly. Have that in writing before you book travel. The intervals before flying are under 'After surgery and daily care' above.
Between trips and after you go home
We try to arrange a check with a dentist in your own country between the stages, and write it into the plan. This may not be possible everywhere, because some dentists may not want to take over treatment in progress. So the plan also says where to turn if a problem arises in between. If a check at home is planned, ask for the records of the first visit before you fly home. That dentist needs them to see what was done. The Dutch dental association suggests discussing your plan with your own dentist21 before you go. It also suggests asking whether you can go to them if something goes wrong.
Before you fly home, ask for your record: the implant system placed, with its diameter and length, and your X-rays and scan. Ask for your aftercare plan in writing too. A dentist at home needs them to look after the implant. In Turkey, the health tourism regulation entitles international patients to an itemised bill. On request, they also get free copies of the records of the materials used, the tests and the imaging22.
Problems after you return are usually first seen by a dentist where you live, and that dentist may not take over work done elsewhere. What a health service or an insurer covers after treatment abroad differs from country to country. Before you travel, ask the health service or your insurer in the country where you live. Ask what they would cover if the implant needs care at home.
Questions to ask before you commit
These are the questions we suggest you ask before treatment abroad. Ask us all of them, and ask for the answers in writing.
- Who will carry out my treatment, and what are their qualifications?
- How many times have you carried out this procedure; what are your success, complication and infection rates?
- Are you regulated by a professional body and registered with it?
- If there is a complication, are the remake and correction terms in writing, and for how long do they apply?
- What aftercare do you provide, and who can I contact after the treatment?
- What happens if I am unhappy with the results?
- If there are complications, who pays for the further treatment, the extra flights and the hotel?
- Do you have a complaints system, and can I see a copy?
We publish no implant figures of our own yet. Ask us for them, and ask how complications were defined and over what period.
Dental regulation differs between countries; check the rules in your own country as well. The full list of questions to ask before treatment abroad is on our page about dental treatment abroad. We give you the route to follow if there is a complication, and our remake terms, in writing before treatment. You can ask us for that document before you decide. You can take time to decide. You can say no, or ask to stop, at any stage, including after the examination. Ask before you travel what you would pay if the examination shows that an implant does not suit you. Having the treatment with a dentist where you live remains an option.
When to contact a dentist
Contact your dentist after surgery, or at any time once the implant is in use, if you notice any of the following.
- Pain or swelling increases after the third day, or bleeding does not stop
- Numbness of the lip, tongue or chin lasts beyond the expected duration of the anaesthetic
- The implant or crown moves, a screw feels loose, or a piece cracks or breaks
- Bleeding, a bad smell, pus or receding gum around the implant
- A high temperature or feeling unwell after surgery
- Pain on biting, or the bite feels high
- Nasal discharge, a blocked nose or sinus pain on the side of an implant in the back of the upper jaw
Before you fly home. If any of these starts while you are still in Turkey, tell us before you travel.
Once you are home. Contact us through the route written in your plan. If numbness persists, pain or swelling keeps increasing, or the implant moves, also see a dentist locally without waiting for our reply. If your plan names a dentist at home, contact them as well.
Emergencies. Do not wait for the clinic's reply if breathing or swallowing becomes difficult. The same applies to rapidly spreading swelling of the face or neck, or swelling around the eye. Go to the nearest emergency department or call the emergency number where you are (112 if you are in Turkey).
What determines the cost?
This page carries no prices. The main things that shape a plan are:
- How many teeth are missing and where; whether extractions are needed
- Whether bone grafting or a sinus lift is needed
- The number of implants, the system chosen and the abutment that goes on it
- The material of the crown or bridge
- The temporary solution used during the waiting period
- Sedation; the number of trips and the review programme
- The remake terms if there is a complication
Ask for three things in writing. What does your plan include? Which items are left 'to be decided later'? Who pays for further treatment and extra travel if there is a complication? Two quotes for the same procedure may not describe the same scope. Add travel and accommodation for each trip when you compare them.
Which option suits your missing tooth?
Send a panoramic X-ray or scan if you have one, and photographs of your teeth. Our dentists will write back on the options, how many stages and trips are likely, and whether bone support may be needed; the definitive plan follows an examination and a 3D scan.
Frequently Asked Questions
What type of implants will you use?
The system planned for you, and its diameter and length, should be written in your treatment plan; ask for them in writing. The 2017 consensus report on diseases around implants noted that there is no generic implant9: there are numerous designs, with different surfaces. Two things matter as much as the brand name. Can the parts still be obtained years later, including by a dentist in your own country? And will you be given a record of the implant?
Is a temporary solution available? Will the temporary teeth be fixed?
There are four ways. The gap can be left empty, or you can have a removable temporary denture or a temporary bridge bonded to the neighbouring teeth. In selected patients, a temporary tooth goes on the implant. The last is not for everyone; the implant must hold firmly enough at placement. The Cochrane review found no convincing difference10 within one year between immediate and delayed loading. Another review reported slightly lower survival11 with immediate loading. If you are travelling, this is what you will wear at home between trips, so settle it before you book.
How long does healing take, and why is it not the same for everyone?
How long an implant needs to fuse with the bone depends on bone density, its position, any graft and how you heal. It is often shorter in the lower jaw than in the upper, and longer if a graft was done. For orientation, the Cochrane review calls a restoration fitted more than two months after placement10 conventional loading. Fitting it earlier is done only in selected cases. Ask for the reasoning behind the period you are given: which area of bone, whether there is a graft, whether you smoke. A shorter period is not right just because another clinic quoted one.
Why is the extraction necessary? Can my tooth be saved?
This question comes before the implant. If root canal treatment, gum treatment, repair of a fracture or a crown could keep the tooth, that is assessed first. Ask for the reason for extraction: a root fracture, advanced bone loss, or decay that cannot be repaired. Ask to be shown the reason on the scan and at the examination. If it is still unclear, ask another dentist, for example your dentist at home, for a second opinion.
How many visits to Antalya will I need? Another clinic said two.
Usually at least two, because the implant has to heal before the final crown or bridge is made. Some plans need a third, for example when a graft is needed first. The restoration can be fitted immediately (within one week), early (between one week and two months) or after the conventional wait10. The timing depends on how firmly the implant holds, the bone and the bite. Ask separately whether the tooth fitted is temporary or final; they are not the same thing. Before you compare the number of trips, ask in writing which stages each visit covers and how long the gap between them is. A 2023 narrative review suggests waiting at least 72 hours after implant placement before flying17. It assumes no pain, swelling or bleeding at the site. It is the shortest wait before flying, not the length of the whole treatment.
Is an immediate implant possible?
Placing the implant in the same session as the extraction is possible in some cases. In one review, survival was 95.2 percent15 for implants placed straight into the extraction socket. For implants placed in healed bone it was 98.4 percent15 (per implant). So in that review, more implants were lost when placed in the same session as the extraction. The review's authors ask for the method to be used with caution. Whether it is possible depends on infection at the site, the state of the bone wall and what you expect from the appearance.
Is an implant the same as a crown or a veneer?
No. An implant replaces the root of a missing tooth and is placed in the jawbone. A crown or a veneer is made on a tooth that is still in the mouth. A crown is also fixed on top of an implant, which is why they get confused. If your tooth is still there, the first question is whether it can be saved. If it can, how it is restored depends on the damage: a filling, a crown or another restoration, sometimes after root canal or gum treatment. A crown covers most of the tooth, while a veneer mostly covers its front surface. They serve different purposes, and one does not replace the other. If the tooth cannot be saved, an implant is among the options after extraction.
How long do dental implants last?
In a 46-study review, of every 100 implants about 97 were still in the mouth after five years and about 95 after ten12. Of every 100 crowns on them, about 96 were in use after five years and about 89 after ten12. These are averages across countries, not our own results. The ten-year values are estimates from a statistical model, based on studies with a mean follow-up of at least five years12. An offer that promises a lifetime result is not based on evidence.20
What decides the cost?
This page gives no prices. The main items are the missing teeth and where they are, extractions, bone support, and the number and system of implants. The crown material, the temporary solution, sedation, the number of trips and the review programme also count. When you compare two quotes, compare the scope. What is included, what is left for later, and who pays for further treatment and travel after a complication?
What if something goes wrong after I go home?
If breathing or swallowing becomes difficult, or swelling spreads quickly or reaches the eye or neck, get emergency care where you are. Then tell us. For a high temperature or bleeding that does not stop, contact a dentist straight away. For other problems, contact us through the route in your plan. If numbness persists, pain or swelling keeps increasing, or the implant moves, also see a local dentist without waiting for our reply. The route to follow if there is a complication is given to you in writing before treatment, including who pays for further treatment and travel. We try to arrange a check with a dentist in your own country, but this may not be possible everywhere. Before you travel, ask the health service or your insurer in the country where you live. Ask what they would cover if the implant needs care at home.
Can an implant get a cavity?
No. Decay is a disease of natural tooth tissue. An implant and the crown on it are not tooth tissue, so they do not decay. Your natural teeth, including those next to the implant, can still decay. The gum and bone around an implant can also become inflamed. Peri-implant mucositis is inflammation of the soft tissue alone, without loss of the supporting bone; it is considered a forerunner of peri-implantitis23. In peri-implantitis the supporting bone is also lost; if it is not controlled, the implant can be lost. Daily cleaning, including between the teeth, and regular reviews help prevent both decay and this inflammation. An international consensus report recommends an X-ray and probing measurements as a baseline9 when the restoration is complete. The European Federation of Periodontology guideline calls for a structured supportive care programme18. Have bleeding, swelling or pus around the implant checked.
Does getting an implant hurt?
The surgery is done under local anaesthetic, which numbs the area. Conscious sedation can be added if you want it and it suits you. Once the anaesthetic wears off, soreness, swelling and bruising can follow in the first days, then settle. Use cold packs and the painkillers your dentist advises. A Cochrane overview looked mostly at trials after wisdom tooth removal. It found ibuprofen and paracetamol (called acetaminophen in some countries) taken together24 among the non-prescription options that worked well. If you take blood thinners or other medicines, ask which painkiller suits you. Contact your dentist if pain or swelling is still increasing after the third day, or if bleeding does not stop. Difficulty breathing or swallowing, or fast-spreading swelling of the face or neck, needs emergency care.

Dt. Dilek AKSU GÜLER
Dentist · Founder
She has completed advanced training in implantology and works in aesthetic restorations and smile design.
Sources
- Levels of smoking and dental implants failure: systematic review and meta-analysis (23 articles). Journal of Clinical Periodontology 2020;47(4):518-528. 2020.↩doi.org
- Smoking in relation to early dental implant failure: systematic review and meta-analysis (32 observational studies, 59,246 implants, 14,115 patients). Journal of Dentistry 2024;151:105396. 2024.↩doi.org
- Effectiveness of implant therapy in patients with and without a history of periodontitis: systematic review with meta-analysis of prospective cohort studies (14 studies, >=36 months). Journal of Periodontal Research 2025;60(6):524-543. 2025.↩doi.org
- Bruxism and dental implants: systematic review and meta-analysis (27 studies; 2,105 implants in probable bruxers, 10,264 in non-bruxers). Journal of Oral Rehabilitation 2024;51(1):202-217. 2024.↩doi.org
- Impact of hyperglycemia on the rate of implant failure and peri-implant parameters in patients with type 2 diabetes mellitus: systematic review and meta-analysis (9 studies). Journal of the American Dental Association 2021;152(3):189-201. 2021.↩doi.org
- The impact of diabetes on dental implant failure: a systematic review and meta-analysis. International Journal of Oral and Maxillofacial Surgery 2016;45(10):1237-1245. 2016.↩doi.org
- Diabetes mellitus and dental implants: systematic review and meta-analysis (89 publications; 5,510 implants in diabetic and 62,780 in non-diabetic patients). Materials 2022;15(9):3227. 2022.↩doi.org
- Effects of bisphosphonates and denosumab on dental implants: systematic review with meta-analysis (21 studies, ROBINS-I, GRADE). Oral Diseases 2025;31(10):2835-2847. 2025.↩doi.org
- Peri-implant diseases and conditions: consensus report of workgroup 4 of the 2017 World Workshop on the Classification of Periodontal and Peri-Implant Diseases and Conditions. Journal of Clinical Periodontology 2018;45 Suppl 20:S286-S291. 2018.↩doi.org
- Interventions for replacing missing teeth: different times for loading dental implants (Cochrane review, 26 RCTs, 1,217 participants, 2,120 implants). Cochrane Database of Systematic Reviews 2013;(3):CD003878. 2013.↩doi.org
- Immediate versus early or conventional loading dental implants with fixed prostheses: systematic review and meta-analysis of randomized controlled trials (39 RCTs). Journal of Prosthetic Dentistry 2019;122(6):516-536. 2019.↩doi.org
- Systematic review of the survival rate and the incidence of biological, technical and aesthetic complications of single crowns on implants (46 studies, mean follow-up 5 years). Clinical Oral Implants Research 2012;23 Suppl 6:2-21. 2012.↩doi.org
- What is the prevalence of peri-implantitis? A systematic review and meta-analysis (57 articles, 2005-2021). BMC Oral Health 2022;22(1):449. 2022.↩doi.org
- Peri-implant health and disease. A systematic review of current epidemiology (11 studies). Journal of Clinical Periodontology 2015;42 Suppl 16:S158-S171. 2015.↩doi.org
- Immediate implant placement into fresh extraction sockets versus delayed implants into healed sockets: systematic review and meta-analysis. International Journal of Oral and Maxillofacial Surgery 2017;46(9):1162-1177. 2017.↩doi.org
- Standards for Conscious Sedation in the Provision of Dental Care (V1.1). Intercollegiate Advisory Committee for Sedation in Dentistry, Dental Faculties of the Royal Colleges of Surgeons and the Royal College of Anaesthetists, 2020. 2020.↩saad.org.uk
- Dental tourism and the risk of barotrauma and barodontalgia (narrative review with guiding principles). British Dental Journal 2023;234(2):115-117. 2023.↩doi.org
- Prevention and treatment of peri-implant diseases: the EFP S3 level clinical practice guideline. Journal of Clinical Periodontology 2023;50 Suppl 26:4-76. 2023.↩doi.org
- Dental checks: intervals between oral health reviews (clinical guideline CG19). National Institute for Health and Care Excellence, published 27 October 2004. 2004.↩nice.org.uk
- Comparison of survival and complication rates of tooth-supported fixed dental prostheses and implant-supported fixed dental prostheses and single crowns. Clinical Oral Implants Research 2007;18 Suppl 3:97-113 (erratum 2008;19(3):326-8). 2007.↩doi.org
- Naar de tandarts in het buitenland? Wees op je hoede!. KNMT / Allesoverhetgebit.nl, 13 April 2026. 2026.↩allesoverhetgebit.nl
- Uluslararasi Saglik Turizmi ve Turistin Sagligi Hakkinda Yonetmelik. T.C. Saglik Bakanligi, Resmi Gazete 26/4/2025, No 32882. 2025.↩resmigazete.gov.tr
- Peri-implant mucositis (narrative review for the 2017 World Workshop). Journal of Clinical Periodontology 2018;45 Suppl 20:S237-S245. 2018.↩doi.org
- Non-prescription (OTC) oral analgesics for acute pain: an overview of Cochrane reviews. Cochrane Database of Systematic Reviews 2015;(11):CD010794. 2015.↩doi.org
Specialists Who Perform This Treatment
Dt. Dilek AKSU GÜLER
She has completed advanced training in implantology and works in aesthetic restorations and smile design.

Dt. Furkan ALTINEL
Dentist; aesthetic dentistry, implants and prosthetic treatments

Dt. Hakan AKMAN
Specialty training at the Department of Oral and Maxillofacial Surgery, Ankara University (1996-2003).

Uzm. Dt. İsmail KILIÇ
Prosthodontics Specialist; aesthetic dentistry, digital smile design and implants