
What is a deep cleaning?
A deep cleaning is the removal of plaque and tartar that have built up on the root surfaces, in the pockets below the gum, in periodontitis. Dentists call it subgingival cleaning, or scaling and root planing; in Turkey it is widely known as küretaj. The European guideline recommends this procedure as the second step1 of treatment for periodontitis.
A routine scale and polish is aimed mainly at deposits above the gum line; a deep cleaning systematically targets the inside of the pockets the disease has created. Someone with healthy gums does not need a deep cleaning. Cleaning can bring the disease under control, but it does not bring back2 the tissue periodontitis has destroyed. For the overall picture of gum disease, see the gum disease page.
- A deep cleaning is for periodontitis; if your gums are healthy, you do not need one.
- You may have sensitivity in the following days; as the gums heal, the root surfaces can become more visible.
- It is not a one-off procedure: re-assessment and regular supportive care follow.


Who needs it, and who does not?
When it may be needed
- People found to have periodontitis at an examination. Which areas are cleaned is decided by looking at the pocket measurements and the bleeding.
- Pockets that bleed again or become deeper during supportive care after treatment for periodontitis
When it is not needed, or something else is considered first
- Healthy gums. A deep cleaning is not needed. Tartar above the gum line can be cleaned at check-ups; your dentist decides how often.
- Gingivitis only. Gingivitis can be reversed with better oral hygiene2. Cleaning above the gum line and improving your oral hygiene is often enough.
- Receding gums without signs of disease. The receded area can be monitored3; cleaning does not reverse recession.
Situations that need care
Routine cleaning, deep cleaning and other options
- Doing nothing. In periodontitis, the tartar below the gum stays where it is; tartar does not dissolve6 at home with a toothbrush, toothpaste or mouthwash.
- Improving oral hygiene. This is the basis of every step, but on its own it does not remove tartar below the gum.
- Routine scale and polish. This mainly cleans plaque and tartar above the gum line. There are studies of adults without severe gum disease who attend regular check-ups. These studies compared a routine scale and polish every 6 or 12 months with no scheduled scale and polish. Over 2 to 3 years, the routine cleaning made little or no difference7 to gingivitis. It reduced tartar slightly; the clinical importance of this is unclear. This result is based on 2 studies of 1,711 adults in the United Kingdom, and the certainty of the evidence is high.
- Deep cleaning (below the gum). In periodontitis, this cleans the inside of the pockets and the root surfaces.
- Air-polishing. In small studies during the care period after treatment, compared with hand and ultrasonic instruments, it showed no statistically significant difference8 in pocket depth. This does not mean the two methods are equivalent; most of the studies carry a high risk of bias. In studies using glycine or erythritol powders, the discomfort patients reported was similar or lower9 than with hand or ultrasonic instruments. There is no evidence that it removes established tartar on its own.
- Periodontal surgery. This is considered for pockets that stay deep after a deep cleaning.
- Mouthwash and antibiotics. Chlorhexidine mouthwash reduces plaque, but it is used only for a short time and it does not remove tartar below the gum. Additional antibiotics or laser are not among the topics we give sources for on this page; if they are suggested, ask your dentist why.
| Routine scale and polish | Deep cleaning | |
|---|---|---|
| What does it clean? | Mainly above the gum line | The pockets below the gum and the root surfaces |
| Who is it for? | People with healthy gums or gingivitis | People with periodontitis |
| Anaesthetic | Usually not needed | Usually local anaesthetic |
| Afterwards | Regular check-ups | Re-assessment and supportive care |
How is a deep cleaning done?
The steps below are for cleaning below the gum as part of treatment for periodontitis. The whole mouth can be cleaned in one session or section by section. How many appointments you need and which route is chosen are planned together after the examination, depending on how widespread the disease is, your health and your preference.
Examination and measurement
The gum pockets are measured with a thin probe; bleeding points and loose teeth are recorded. X-rays are taken if needed.
Preparation
You are shown how to brush and clean between your teeth in the way that suits you, and plaque and tartar above the gum line are cleaned off. Tell your dentist about the medicines you take and any illnesses you have.
Cleaning below the gum
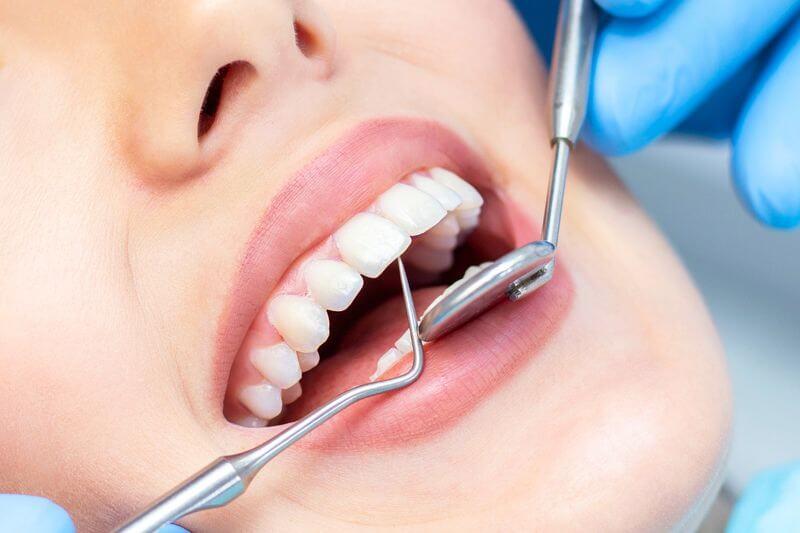
Usually under local anaesthetic, plaque and tartar are cleaned away from inside the pockets and from the root surfaces with hand instruments or ultrasonic instruments.
Re-assessment
Once the gums have healed, the pockets are measured again. For pockets that stay deep, the cleaning can be repeated or surgery is discussed.
Supportive care
Regular check-ups and professional cleaning. The interval is set according to your risk.
Risks and benefits
Risks and side effects
- Sensitivity. In the days after the procedure, your gums may be tender and your teeth sensitive to hot and cold. We cannot say on this page how often this happens or how long it lasts. If the sensitivity continues, see your dentist10 to rule out other causes such as decay. For dentine sensitivity, toothpastes containing stannous fluoride or arginine are recommended among the first options11. This recommendation is based on studies of dentine sensitivity in general; it is not specific to the period after a deep cleaning.
- Gums that look receded. As the inflammation settles and the swelling goes down, the gum margin can sit lower and root surfaces can be exposed. You may feel gaps between your teeth.
- Bleeding. In the first days there may be slight bleeding when you brush.
- Air escaping into the tissues (emphysema). Air escaping into the tissues during dental treatment is an infrequently reported complication12. The case reports include tooth cleaning and air-polishing. Swelling that appears suddenly after treatment and crackles when touched should be checked straight away.
- Chlorhexidine mouthwash. If recommended, it is used for a short time. Used for 4 to 6 weeks, it stains the teeth13; altered taste and irritation inside the mouth have also been reported.
Benefits
- Periodontitis can be brought under control and gum health can be restored14. Bone that has been lost, however, largely does not grow back.
- In people with periodontitis and diabetes (mostly type 2), gum treatment lowered HbA1c by 0.43 percentage points on average15 at 3 to 4 months; HbA1c is the long-term measure of blood sugar. This result is based on 30 studies and 2,443 participants, and the certainty of the evidence is moderate. It does not replace diabetes treatment.
At the re-assessment, your dentist measures the pockets again to see how your gums have responded.
How will you feel afterwards, and how should you care for your teeth?
Do not eat until the anaesthetic has worn off; you could bite your lip or cheek without noticing. In the first days your gums may be tender and bleed a little when you brush. Do not stop brushing; carry on with gentle movements.
Daily care
- Brush your teeth at least twice a day with a fluoride toothpaste. After brushing, spit the toothpaste out and do not rinse16 your mouth with water.
- For most people, a toothbrush with a small head and medium bristles17 is suitable.
- Clean between your teeth every day. For people who have been treated for periodontitis, interdental brushes are recommended as the first choice1; floss is an option where the brush does not fit.
- If your teeth are sensitive, rub a small amount of sensitivity toothpaste onto the sensitive area with your finger and avoid10 acidic food and drinks.
- Use chlorhexidine mouthwash only if your dentist recommends it, and only for a short time.
- If you smoke, ask for support to stop.

How long does the effect last?
A deep cleaning is not a one-off solution. In someone whose periodontitis has been treated, the risk of the disease coming back remains increased14, and it needs close monitoring.
The European guideline recommends a supportive care interval of at least 3 and at most 12 months1, depending on the person's risk. Regular professional cleaning is also recommended as part of this care. Keeping your appointments and cleaning between your teeth every day at home are the way to keep the result.
When should you see a dentist?
Contact your dentist if any of the following happens after a deep cleaning:
- Pain or swelling that does not ease within a few days, or keeps getting worse
- Bleeding that does not stop
- A fever
- Sensitivity that has not eased after several weeks
- Teeth becoming more and more loose
Swelling that appears suddenly after treatment and crackles when touched should be checked without waiting12; if you cannot reach your dentist straight away, go to a hospital emergency department.
Emergencies. The following need urgent medical help18. Do not wait for a dental appointment; go to a hospital emergency department or call 112:
- Swelling that makes it hard to breathe, speak or swallow
- Swelling of the eye or the neck19, a painful eye, or sudden problems with your eyesight
- A lot of swelling inside the mouth
- Finding it hard to open your mouth
What determines the cost?
This page does not give prices. Your treatment plan is prepared for you after the examination. The main factors that shape the plan are:
- In how many areas and on how many teeth cleaning below the gum is needed
- How many appointments it takes and whether anaesthetic is needed
- X-rays, if needed
- Re-assessment, surgery if needed, and supportive care appointments
Ask for the plan in writing, showing what is included and which procedures will be assessed separately.
Frequently Asked Questions
How long does a deep cleaning take, and how many visits?
It depends on how widespread the disease is. The whole mouth can be cleaned in one session or section by section over several appointments. How many appointments you need is planned after the examination; ask for the plan in writing.
Does a deep cleaning hurt?
Cleaning below the gum is usually done under local anaesthetic. In the following days your gums may be tender and your teeth sensitive to hot and cold. Increasing pain, swelling or a fever are not normal; contact your dentist.
What happens if I do not have a deep cleaning?
Tartar below the gum does not dissolve at home and stays where it is. If periodontitis progresses, the tissues that hold the tooth break down, and this damage is irreversible2. Teeth can become loose and be lost.
How often should I have my teeth scaled and polished?
In adults without severe gum disease who attend regular check-ups, routine cleaning has been compared with no scheduled cleaning. A routine scale and polish every 6 or 12 months made little or no difference7 to gingivitis. It reduced tartar slightly; the clinical importance of this is unclear. For people who have been treated for periodontitis, the supportive care interval is set at 3 to 12 months1 according to risk.
Does a deep cleaning whiten teeth?
No. A deep cleaning is not a whitening treatment. Once tartar and surface stains are cleaned off, your teeth may look lighter, but the tooth's own colour does not change. To lighten the colour of your teeth, see the teeth whitening page.
Can air-polishing replace a deep cleaning?
There is no evidence8 that air-polishing removes established tartar on its own. Small studies during the care period that compared it with hand instruments found no significant difference; this does not mean they are equivalent. In studies using glycine or erythritol powders, the discomfort patients reported was similar or lower.
Will my gums be the same as before after a deep cleaning?
The inflammation settles and gum health can be restored. However, bone destroyed by periodontitis largely does not grow back, and as the inflammation settles the gum margin can sit lower. Regular supportive care is needed to keep the result.

Dt. Dilek AKSU GÜLER
Dentist · Founder
She has completed advanced training in implantology and works in aesthetic restorations and smile design.
Sources
- Treatment of stage I-III periodontitis - the EFP S3 level clinical practice guideline. Journal of Clinical Periodontology 2020;47 Suppl 22:4-60 (erratum 2021;48:163). 2020.↩doi.org
- Prevention and Treatment of Periodontal Diseases in Primary Care, 2nd edition. Scottish Dental Clinical Effectiveness Programme (SDCEP), February 2024. 2024.↩periodontalcare.sdcep.org.uk
- Mucogingival conditions in the natural dentition: narrative review, case definitions, and diagnostic considerations. Journal of Clinical Periodontology 2018;45 Suppl 20:S190-S198. 2018.↩doi.org
- Delivering Better Oral Health, Chapter 5: Periodontal diseases. Department of Health and Social Care / NHS England et al., updated 10 September 2025. 2025.↩gov.uk
- SDCEP: Anticoagulant or antiplatelet medication and your dental treatment (information for patients). Scottish Dental Clinical Effectiveness Programme (SDCEP), March 2022. 2022.↩sdcep.org.uk
- Dental Floss/Interdental Cleaners (Oral Health Topics). American Dental Association, last updated August 2026. 2026.↩ada.org
- Routine scale and polish for periodontal health in adults. Cochrane Database of Systematic Reviews 2018;12:CD004625. 2018.↩doi.org
- Efficacy of air polishing in comparison with hand instruments and/or power-driven instruments in supportive periodontal therapy and implant maintenance: a systematic review and meta-analysis. BMC Oral Health 2022;22:85. 2022.↩doi.org
- A systematic review on the patient perception of periodontal treatment using air polishing devices. International Journal of Dental Hygiene 2016;14(1):4-14. 2016.↩doi.org
- SDCEP Management of Acute Dental Problems: Dentine hypersensitivity. Scottish Dental Clinical Effectiveness Programme (SDCEP). 2026.↩acutedentalproblems.sdcep.org.uk
- Dentifrice formulations for the treatment of dentin hypersensitivity: a systematic review and network meta-analysis. Periodontology 2000, 2026 (Gormley AJ et al.). 2026.↩doi.org
- Dental Procedure-Related Emphysema: A Scoping Review of Clinical Presentation, Anatomical Distribution, Management, and Outcomes. Dental Journal (Basel) 2026;14(9):602. 2026.↩doi.org
- Chlorhexidine mouthrinse as an adjunctive treatment for gingival health. Cochrane Database of Systematic Reviews 2017;3:CD008676. 2017.↩doi.org
- Periodontal health and gingival diseases and conditions on an intact and a reduced periodontium: consensus report of workgroup 1 of the 2017 World Workshop. Journal of Clinical Periodontology 2018;45 Suppl 20:S68-S77. 2018.↩doi.org
- Treatment of periodontitis for glycaemic control in people with diabetes mellitus. Cochrane Database of Systematic Reviews 2022;4:CD004714. 2022.↩doi.org
- Gum disease. NHS, page last reviewed 20 April 2026. 2026.↩nhs.uk
- Delivering Better Oral Health, Chapter 8: Oral hygiene. Department of Health and Social Care / NHS England et al., updated 10 September 2025. 2025.↩gov.uk
- NHS: Dental abscess. NHS (nhs.uk). 2026.↩nhs.uk
- NHS: Toothache. NHS (nhs.uk). 2024.↩nhs.uk